

Ptosis Correction in Seoul, Korea
Customized design for the most important part of your facial impression, restoring your natural beauty.
Ptosis Correction
Transforming a tired, drowsy appearance into a bright, alert look. By strengthening the levator palpebrae superioris — the muscle responsible for lifting the eyelid — the iris is corrected to 80–90% exposure. Frontal compensatory wrinkling caused by using the forehead to open the eyes also improves, brightening the overall expression.
Quick Facts
| Procedure | Ptosis Correction · Ptosis Correction |
|---|---|
| Surgeon | Dr. Seungsoo Kim (Board-certified Plastic Surgeon, 10+ yrs) |
| Time | 1 hour |
| Anesthesia | IV Sedation |
| Hospitalization | Not required |
| Stitch Removal | 5–7 days post-op |
| Follow-up Visits | 2–3 visits |
| Recovery | From 1 week post-op |
| Best For | Using the forehead or brow to help open the eyes · Frequently told that you look tired or sleepy · Iris exposure of less than 70% · Noticeable size difference between the two eyes (asymmetry) |

Check Point Highly Recommended For
Ptosis Correction Procedure
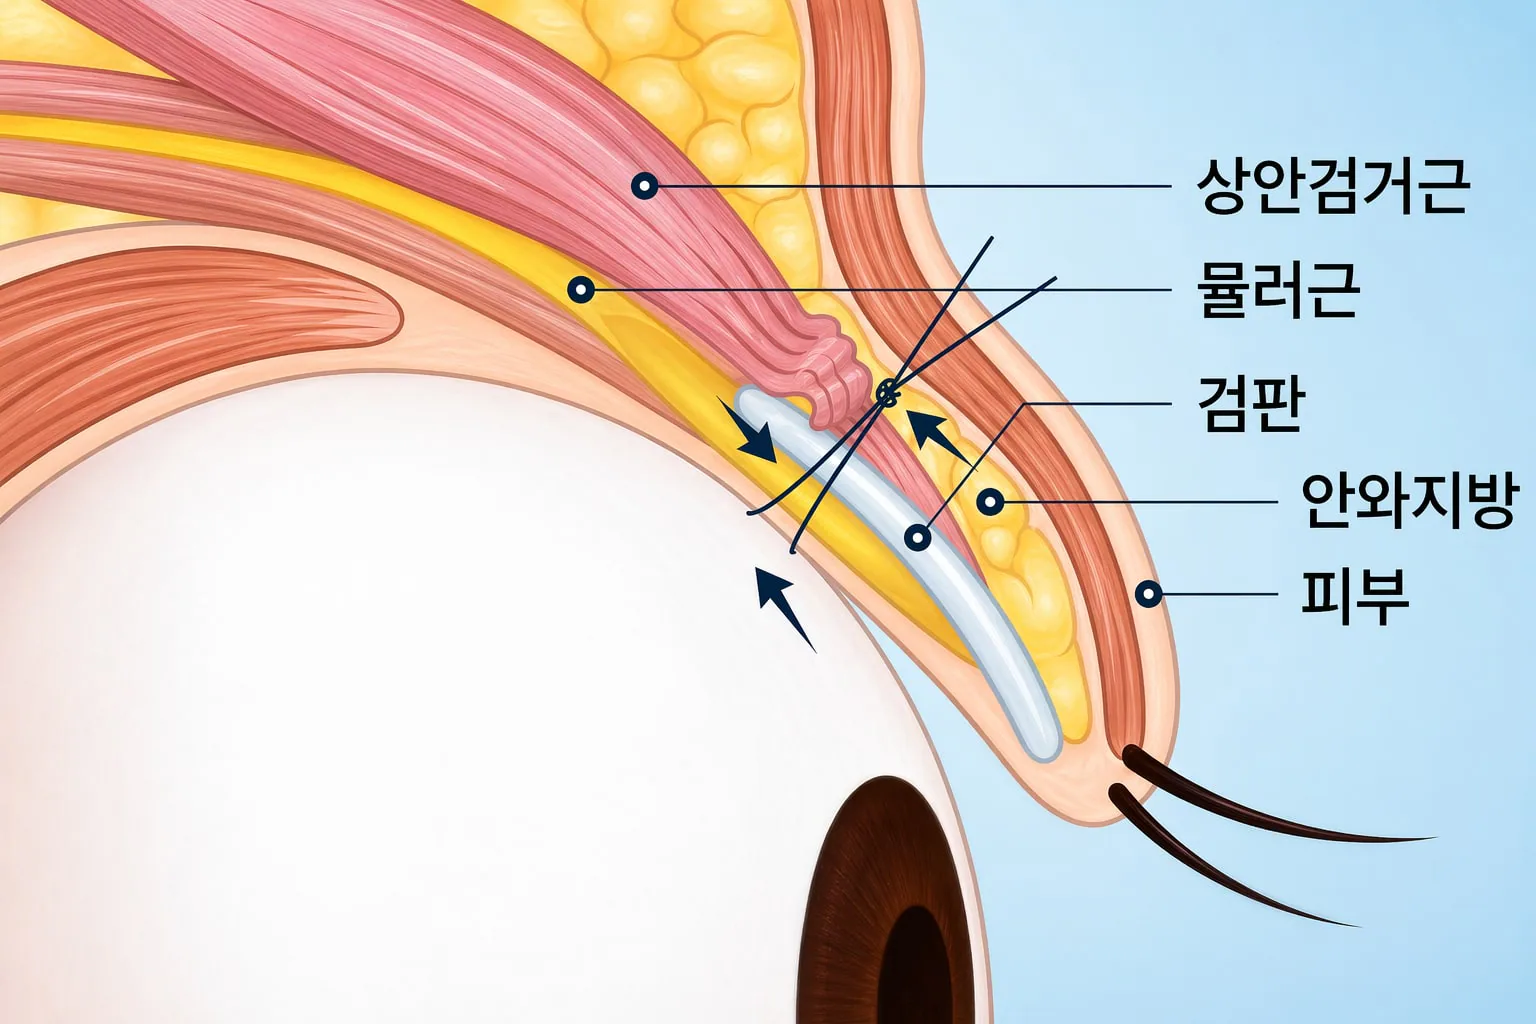
Precise Assessment
The degree of ptosis and levator muscle strength are measured to determine the ideal iris exposure target.
Muscle Access
Through the incision line, the levator palpebrae superioris and Müller's muscle — the key lid-elevating muscles — are exposed.
Tension Adjustment (Key Step)
The weakened muscle is tightened and secured under appropriate tension so that the iris is visible at 80–90%.
Final Result
Bilateral symmetry and definition are confirmed, then fine suturing completes the refreshed, open eye contour.
Non-Incision vs Incision Ptosis Correction — Which Is Right for You?
The appropriate technique is determined by the degree of ptosis (in mm) and the presence of bilateral asymmetry. Incision-based correction is essential for ptosis of 1 mm or more.
| Criteria | Non-incisional ptosis repair | Incisional ptosis repair |
|---|---|---|
| Indication Criteria | Ptosis less than 1 mm (near-normal levator function) | Ptosis 1 mm or more (essential indication) |
| Bilateral Asymmetry | Mild asymmetry only | Essential for significant asymmetry (precise bilateral correction achievable) |
| Surgical Technique | Suture passed internally to engage the levator once | Direct levator resection and fixation via incision |
| Degree of Effect | Supplementary (slightly easier to open the eyes) | Maximised (iris exposure 80–90%) |
| Scarring | None | Concealed within the crease line (virtually invisible) |
| Surgery Time | 30 minutes | 1 hour |
| Recovery Period | Fast (3–5 days) | 1 week |
| Recommended For | Adequate levator function but wanting a slightly easier lid opening | Significant ptosis, bilateral asymmetry, or when precise correction and maximum effect are required |
Eye Surgery Procedures — At a Glance
The right method depends on lid thickness, sagging, eye proportion, and revision needs.
| Procedure | Area | Time | Anesthesia | Recovery | Key Technique |
|---|---|---|---|---|---|
| Natural Adhesion Double Eyelid Natural Adhesion | Upper eyelid (double-fold line) | 30 minutes | IV Sedation / Local | From day 3–4 | Micro-tunnel + natural adhesion |
| Incision Double Eyelid Incision Method | Upper eyelid (skin/muscle/fat) | 1 hour | IV Sedation / Local | From 1 week post-op | Incision + tissue trim + line fixation |
| Canthoplasty Canthoplasty | Medial / lateral / lower canthus | 30 minutes | Local / IV Sedation | From 1 week post-op | CPF anchoring + skin redraping |
| Ptosis Correction Ptosis Correction | Upper eyelid (levator muscle) | 1 hour | IV Sedation | From 1 week post-op | Levator strengthening |
| Under-Eye Fat Repositioning Under Eye Fat Repositioning | Lower eyelid (conjunctiva/fat) | 30 minutes – 1 hour | IV Sedation | From 1 week post-op | Conjunctival fat repositioning |
| Revision Eye Surgery Revision Eye Surgery | Eye revision | 1–2 hours | IV Sedation | 2 weeks or more | Adhesion release + redesign |
Click a row to open that procedure.
The AVA Difference
Natural Adhesion Technique
Tissue is repositioned along natural planes and secured at multiple points.
Designed to reduce loosening and align with the patient's intrinsic contour.
Levator Aponeurosis Ptosis Correction
Ptosis is addressed by shortening and refixing the levator aponeurosis,
restoring natural eyelid flow.
Patient Satisfaction Defines Completion
Surgery is complete not when sutures are removed,
but when the patient smiles in front of the mirror.
Ptosis correction strengthens the eyelid-opening muscle (levator) to expose more of the iris and brighten sleepy-looking eyes.
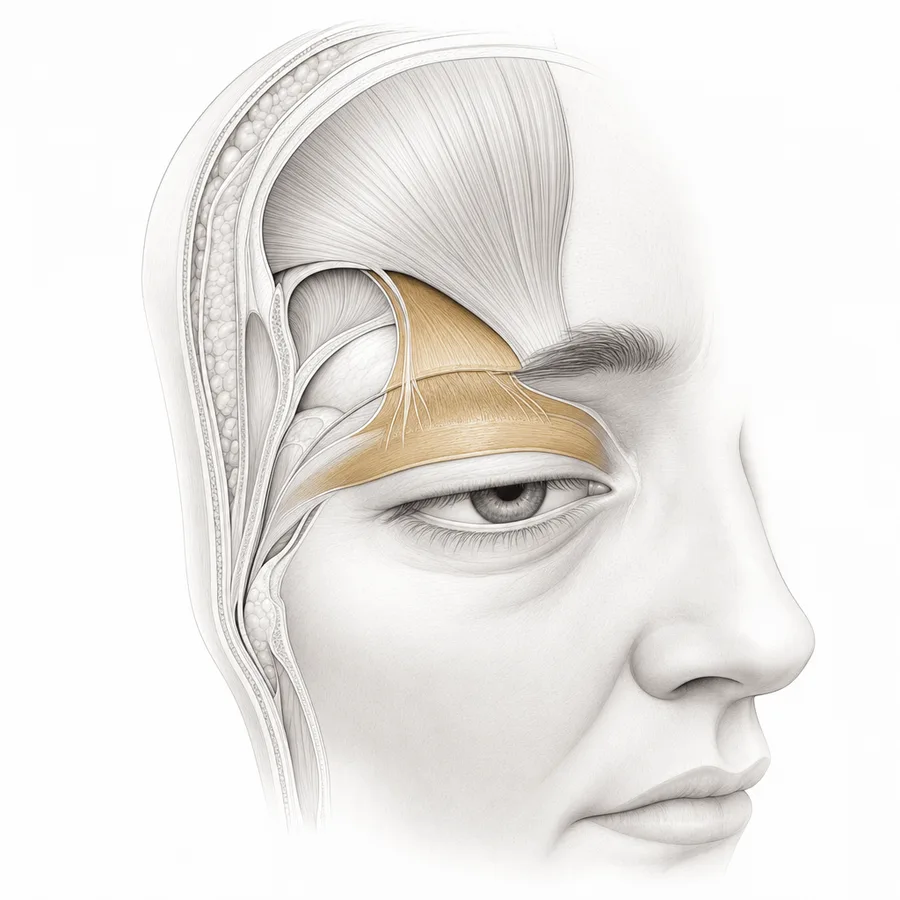
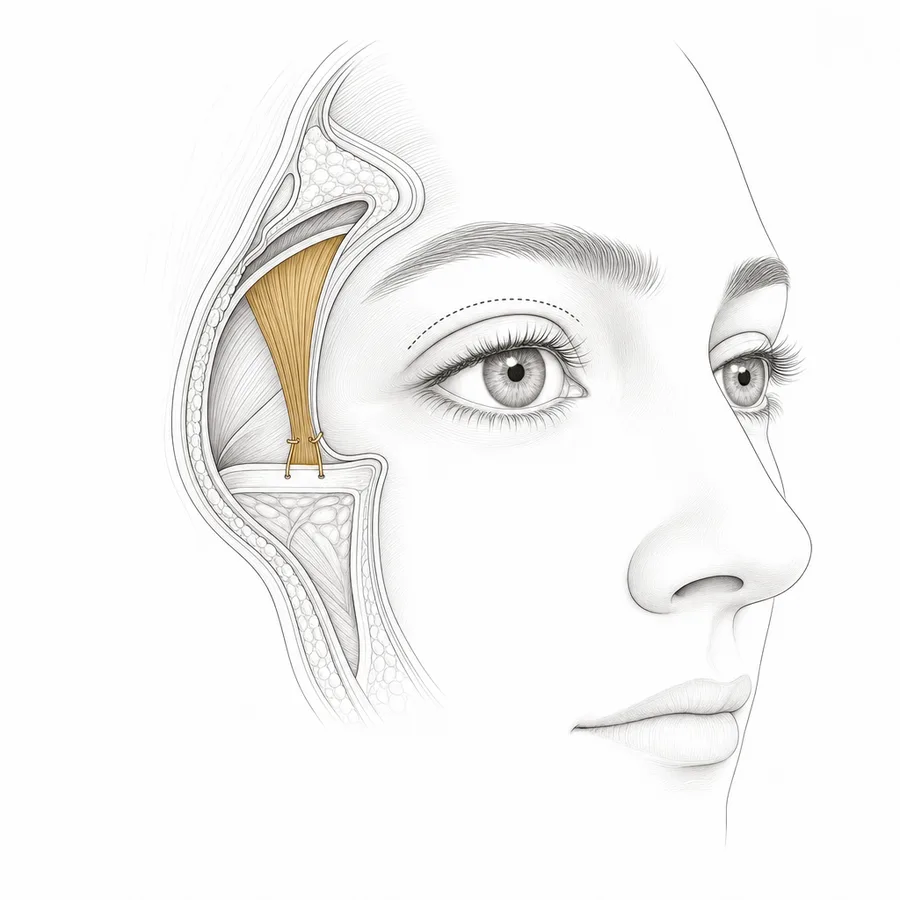 Structure beforeStructure after
Drag to compare
Answer three questions to get a first direction based on the surgeon's logic. For reference only; confirmed at consultation.
Q1.Does your eyebrow sit below the bony rim above the eye?
Q2.Is there enough eyelid skin to touch the lashes?
Q3.Do your eyes look small or sleepy unless you raise your forehead?
Start with a forehead lift
The brow, not the eyelid, has descended. Removing eyelid skin alone pulls the brow lower, so restoring brow position comes first.
Self-check is for reference. Brow position, skin excess and lid-opening strength are measured at consultation.
Ptosis correction
The lid-opening muscle is weak. Removing skin will not open the eye, so the muscle is addressed first.
Self-check is for reference. Brow position, skin excess and lid-opening strength are measured at consultation.
Upper blepharoplasty or sub-brow lift
Brow and muscle are fine; skin excess is the issue. Inner excess suits upper blepharoplasty, outer (corner) excess suits a sub-brow lift.
Self-check is for reference. Brow position, skin excess and lid-opening strength are measured at consultation.
Ptosis correction + upper blepharoplasty
Both muscle weakness and skin excess are present. Incisional ptosis repair shares the same incision as upper blepharoplasty.
Self-check is for reference. Brow position, skin excess and lid-opening strength are measured at consultation.
Surgery may not be urgent
If none apply, the concern may be the crease or the lower lid. Tell us the impression you want at consultation.
Self-check is for reference. Brow position, skin excess and lid-opening strength are measured at consultation.
Who it’s not for
Not advised if eye-opening strength is normal and only the skin has drooped, if you have severe dry eye, since more exposure can make it worse, or if you have a neuromuscular condition such as myasthenia gravis.
What we suggest instead
When drooping skin is the cause, we approach it with upper blepharoplasty or a sub-brow lift.
Pick a surgery date to see stitch removal, return to daily life and the earliest flight home as calendar dates. Confirmed at consultation.
- Arrive in Seoul · consultationD-1Fri, Sep 25
- SurgeryD+0Sat, Sep 26
- Stitch removalD+7Thu, Oct 1
- Back to daily lifeD+7Wed, Sep 30
- Earliest flight homeD+7Thu, Oct 1
- Major swelling settledD+30Mon, Oct 26
Individual recovery and combined procedures change the dates.
Cost depends on the extent of surgery, anesthesia and any combined procedures, and is quoted at consultation. The same criteria apply to every patient.
See current offersQ&A
Post-op Instructions
- Do not rub the surgical area strongly for about a week.
- Avoid alcohol and smoking for at least 2 weeks as they delay recovery.
- Swelling and bruising vary individually but will gradually improve.
- Light walking or stretching helps reduce swelling.
Curious About This Procedure?
Our head surgeon provides a one-on-one assessment and a tailored treatment plan just for you. Results and recovery may vary by individual.